Five papers worth your time — June 3, 2026
The June 2–3 window surfaces five papers across rheumatology, thoracic oncology, breast cancer, infectious disease, and pharmacoepidemiology. Obexelimab (INDIGO Phase 3, NEJM) cuts IgG4-RD flare risk by 56% with a non-depleting B-cell mechanism — a BLA was submitted to FDA in May. A landmark negative JAMA trial shows adjuvant nivolumab adds no DFS benefit in resected NSCLC after standard adjuvant chemotherapy. Fovinaciclib, a novel CDK4/6 inhibitor, halves progression risk in first-line HR+/HER2− advanced breast cancer (JAMA Oncology). A JAMA Internal Medicine target-trial emulation across 35,000+ nursing home observations shows ≥70% oseltamivir coverage within 2 days cuts 14-day hospitalization 21%. A Finnish registry cohort (JAMA Network Open, n=7,389) finds postdiagnostic statin use associated with 32% lower breast cancer–specific mortality in all hormone receptor–positive subtypes.

Today's window is June 2–3, 2026 (approximately 23.5 hours). NEJM, The Lancet main, BMJ main, and Nature Medicine published no new original research articles in this window. The five papers below come from NEJM, JAMA, JAMA Oncology, JAMA Internal Medicine, and JAMA Network Open. Ranking: journal tier combined with estimated citation momentum.
1. Obexelimab cuts IgG4-RD flares by 56% in Phase 3 — NEJM
Journal: New England Journal of Medicine (IF ~180) · Phase 3 double-blind RCT · EULAR 2026 simultaneous presentation · Published June 2, 2026 1
Study design: INDIGO (NCT05662241) enrolled 194 patients with active IgG4-related disease (IgG4-RD) — either newly diagnosed or relapsing — at 114 centers across 19 countries. Patients were 1:1 randomized to obexelimab 250 mg SC weekly × 52 doses or matched placebo. All received standardized glucocorticoid (GC) induction and taper through Week 8. Median age 59 years; two-thirds male; approximately half Asian; over 90% multi-organ involvement. 1
Obexelimab (Zenas BioPharma, ZBIO) is a bispecific monoclonal antibody that co-engages CD19 and FcγRIIb, inhibiting B-cell activation without depleting B cells — mechanistically distinct from both rituximab and inebilizumab (Uplizna, the only currently approved IgG4-RD-specific therapy, granted April 2025). 2

Key findings:
| Endpoint | Obexelimab | Placebo | Result |
|---|---|---|---|
| Time to first adjudicated flare (primary) | — | — | HR 0.44 (95% CI 0.277–0.711); p = 0.0005 |
| 52-week flare-free rate | 73.2% | 45.4% | — |
| Investigator-defined flare (key secondary) | — | — | HR 0.41 (95% CI 0.26–0.66); p = 0.0001 |
| Complete remission at Week 52 | 37.1% | 19.6% | p = 0.0049 |
| Cumulative rescue GC dose | 329.5 mg | 929.8 mg | p = 0.0042 (65% reduction) |
| Grade ≥3 TEAEs | 11.3% | 23.7% | — |
B-cell counts remained at or above the lower limit of normal throughout the trial — the non-depletion mechanism appears maintained in vivo. Thomas Dörner (Charité Universitätsmedizin Berlin), author of the NEJM companion editorial, commented: "Obexelimab provides proof that mimicking natural inhibition of B-cell activation and function is a therapeutic option. Depletion is no longer the only credible B-cell therapeutic paradigm." 2 A BLA was submitted to FDA in May 2026. 1
Clinical implication: The 65% reduction in cumulative rescue GC dose is the number to watch for rheumatologists. IgG4-RD management currently relies on long-term steroids and, increasingly, rituximab or inebilizumab — both of which deplete B cells and carry attendant infection and immunoglobulin deficiency risks. The GC-sparing effect here is adjudicated, not modeled, and the non-depletion mechanism may become a practical differentiator in patients where B-cell depletion is contraindicated. A 3-year open-label extension is ongoing. 1
Funding / affiliation: Zenas BioPharma (industry-funded). Lead investigator: John Stone, Massachusetts General Brigham. 1
Peer review status: Published in NEJM. Industry-funded.
Loading content card…
2. Adjuvant nivolumab shows no DFS benefit in resected NSCLC — JAMA
Journal: JAMA (IF ~120) · Phase 3 open-label RCT · PubMed indexed June 1, 2026 · PMID 42224490 4
Study design: 378-center US National Clinical Trials Network trial (NCT02595994). Enrolled May 2016–September 2019; data cutoff December 2025; median follow-up 72.6 months. 935 patients with fully resected NSCLC (stage ≥ 4 cm and/or N1/N2 node-positive, no sensitizing EGFR or ALK alterations) after completing standard adjuvant chemotherapy ± radiotherapy. Randomized to nivolumab 480 mg IV q4w × 1 year (n = 466) vs observation (n = 469). Median age 66 (nivolumab) and 67 (observation); 52% male in both arms. 4
Key findings:
| Endpoint | Nivolumab | Observation | Result |
|---|---|---|---|
| Median DFS, ITT (co-primary) | 71.3 months | 68.8 months | HR 0.97 (97% CI 0.79–1.20); P = 0.39 |
| Median DFS, PD-L1 ≥50% (co-primary) | 89.8 months | 78.5 months | HR 0.86 (98% CI 0.55–1.34); P = 0.22 |
| Trial disposition | Stopped for futility at 75% information fraction |
Clinical implication: This is the second major negative adjuvant checkpoint trial in NSCLC (following the prior negative perioperative data in some subgroups). The finding matters because nivolumab already has approvals in neoadjuvant and perioperative settings — but this trial tests a distinct clinical scenario: purely adjuvant use after upfront surgery and completed chemotherapy. Neither unselected nor PD-L1–high patients derived DFS benefit. The 72.6-month median follow-up is long enough to capture late recurrence. For thoracic oncologists, this result supports not adding nivolumab after adjuvant chemotherapy completes in the absence of neoadjuvant sequencing, though the comparison between perioperative and purely adjuvant strategies needs further direct evaluation. 4
Funding / affiliation: US National Clinical Trials Network (NCTN). Multi-center US academic consortium. DOI: 10.1001/jama.2026.8992. 4
Peer review status: Published in JAMA. Government/academic-funded (NCTN).
3. Fovinaciclib halves progression risk in first-line HR+/HER2− advanced breast cancer — JAMA Oncology
Journal: JAMA Oncology (IF ~28) · Phase 3 double-blind RCT · PubMed indexed June 1, 2026 · PMID 42224659 5
Study design: POSITIVE trial, 63 centers in China. March 2022–June 2023 enrollment; data cutoff June 2024; median follow-up 16.6 months (range 0.3–27.8). 417 female patients with HR+/HER2− advanced breast cancer, no prior systemic therapy for advanced disease (median age 57 years; range 32–84). Randomized 1:1 to fovinaciclib 200 mg PO QD days 1–21 + aromatase inhibitor (letrozole 2.5 mg or anastrozole 1 mg) QD days 1–28 per 28-day cycle (n = 208) vs matched placebo + AI (n = 209). Premenopausal women received goserelin. 5
Fovinaciclib is a selective CDK4/6 inhibitor (cyclin-dependent kinase 4 and 6) developed by Avanc Pharmaceutical, a subsidiary of Fosun Pharma. CDK4/6 inhibitors — the class established by palbociclib, ribociclib, and abemaciclib — arrest the cell cycle at G1/S. 5
Key findings:
| Endpoint | Fovinaciclib + AI | Placebo + AI | Result |
|---|---|---|---|
| Median PFS (BICR, primary) | Not reached | 20.2 months (95% CI 16.4–NE) | HR 0.55 (95% CI 0.38–0.77); P < 0.001 |
| Discontinuation due to TEAEs | 1.4% (3/208) | 1.4% (3/209) | No difference |
| OS data | Immature (40 events, 9.6%) | — | Not yet reportable |
| EORTC QLQ-C30 (QoL) | Similar longitudinal changes | — | No detriment |
Most common treatment-emergent adverse events were hematologic (consistent with class effects); none led to serious adverse events or discontinuation at a meaningful rate. PFS benefit was consistent across pre-specified subgroups. 5
Clinical implication: CDK4/6 inhibitors are already standard first-line therapy for HR+/HER2− advanced breast cancer globally, so the POSITIVE result is primarily a regulatory data package for fovinaciclib in China rather than a practice change internationally. The HR of 0.55 is numerically consistent with established CDK4/6i class data (palbociclib PALOMA-2: HR 0.58; ribociclib MONALEESA-2: HR 0.56). OS data remain immature and will determine whether this becomes an approved option. The 1.4% TEAE-driven discontinuation rate is lower than reported with the approved agents, though cross-trial comparison is constrained by different definitions and follow-up. 5
Funding / affiliation: Avanc Pharmaceutical / Fosun Pharma (industry-funded). 63 sites, China. DOI: 10.1001/jamaoncol.2026.1938. 5
Peer review status: Published in JAMA Oncology. Industry-funded.
4. Intensive oseltamivir prophylaxis cuts 14-day hospitalization 21% in nursing home flu outbreaks — JAMA Internal Medicine
Journal: JAMA Internal Medicine (IF ~39) · Retrospective cohort / target trial emulation · Published June 1, 2026 (JAMA Intern Med print issue); PubMed PMID 41910957 6
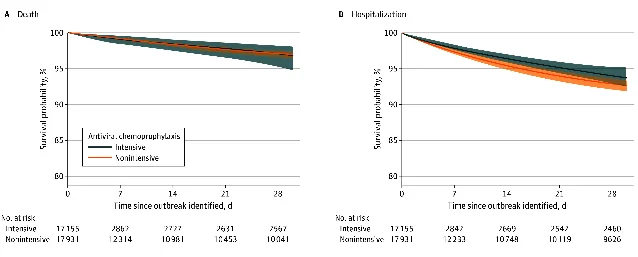
Study design: Sequential cluster-randomized target trial emulation across 12 US nursing home corporations. 404 influenza outbreaks in 318 nursing homes; 35,086 resident-trial observations (29,683 unique residents). Study period: September 2018–May 2022. Population: median age 78 years (IQR 68–86); 60% women; 76% influenza-vaccinated. Outbreak defined as ≥2 laboratory-confirmed influenza cases within 72 hours. 6
- Intensive strategy: oseltamivir chemoprophylaxis for ≥70% of eligible residents within 2 days of outbreak detection (including residents in non-affected units)
- Nonintensive strategy: 0% to <70% coverage within 2 days 7
Key findings:
| Endpoint | Intensive (≥70% coverage) | Nonintensive (<70% coverage) | Result |
|---|---|---|---|
| 14-day hospitalization | 3.58% | 4.54% | RR 0.79 (95% CI 0.64–0.96); RD −0.96% |
| 30-day hospitalization | 6.26% | 7.33% | Not statistically significant |
| 14-day all-cause death | 1.59% | 1.65% | RR 0.96 (95% CI 0.56–1.57); not significant |
| Sensitivity (≥80% coverage) | — | — | RR 0.74 (95% CI 0.59–0.91) |
Extending the prophylaxis initiation window to 7 days showed no significant benefit across coverage thresholds — the timing signal is the key variable, not just the coverage level. 7
Clinical implication: The study authors recommend initiating antiviral chemoprophylaxis for at least 70% of eligible nursing home residents within 2 days of outbreak detection. 7 The absolute risk difference of −0.96% across 35,000+ observations translates to roughly 1 hospitalization prevented per 100 residents in the 14-day window — a clinically relevant magnitude in a population where flu-related hospitalization drives disproportionate downstream morbidity. The absence of a mortality signal at 14 or 30 days may reflect the study's power or the vaccination baseline (76% vaccinated). Non-affected units are often excluded from prophylaxis in current practice; this data supports extending coverage facility-wide from outbreak day.
Funding / affiliation: NIH (Silva); Sanofi and Genentech (co-funders). Lead author: João BB Silva, Brown University. 6 Accompanying editorial: Choi, Inouye, Mody (PMID 41910959). 6
Peer review status: Published in JAMA Internal Medicine. NIH and industry co-funded.
5. Postdiagnostic statins cut breast cancer–specific mortality 32% in hormone receptor–positive subtypes — JAMA Network Open
Journal: JAMA Network Open · Retrospective population-based cohort · Published June 2, 2026 · PMID 42228366 8
Study design: Finnish national registry study, 7,389 female patients with invasive early breast cancer, diagnosed 1995–2013 (median age at diagnosis 60 years; range 21–102). Intrinsic subtyping via surrogate immunohistochemical markers: luminal A-like, luminal B-like (HER2−), luminal B-like (HER2+), and triple-negative. Statin use assessed in two exposure windows — prediagnostic and postdiagnostic — and tested against both breast cancer–specific mortality and all-cause mortality. Statistical analysis performed September–November 2023. 8
Key findings:
| Endpoint | Statin users | Non-users | Result |
|---|---|---|---|
| Breast cancer–specific mortality (postdiagnostic use) | Lower | — | Age-adjusted HR 0.68 (95% CI 0.57–0.82) |
| All-cause mortality (postdiagnostic use) | Lower | — | HR 0.83 (95% CI 0.75–0.92) |
| Prediagnostic statin use | No association | — | Null result |
| Dose-response trend (postdiagnostic) | Present | — | Significant |
| Subtype specificity | HR+ subtypes (all 3) benefit; direction similar in TN | — | Consistent |
Multivariable-adjusted models, one-year lag-time analysis, and adjustment for post-diagnosis cholesterol levels all left the association substantially unchanged. 8
Clinical implication: This is an observational cohort, and unmeasured confounding (healthier patients more likely to receive and adhere to statins; co-medication effects) cannot be excluded. The null prediagnostic finding, the dose-response pattern, and consistency across all three luminal subtypes are the features that lift this above typical statin–outcome noise. For oncologists, the implication is not to start statins for breast cancer survival now — the evidence base for a prospective recommendation is not yet there — but to track whether patients with HR+ disease who are already on statins for cardiovascular indications are being maintained on them through and after chemotherapy, where statin discontinuation is common. 8
Funding / affiliation: Finland-based institutions. Lead authors: Palmi S et al. DOI: 10.1001/jamanetworkopen.2026.16375. 8
Peer review status: Published in JAMA Network Open. Funding not reported in available sources.
Cover image: AI-generated illustrative image.
References
- 1
- 2
- 3PubMed — INDIGO trial protocol (Culver et al., Rheumatol Ther 2026)
pubmed.ncbi.nlm.nih.gov
- 4PubMed — Adjuvant nivolumab vs observation in resected NSCLC (PMID 42224490)
pubmed.ncbi.nlm.nih.gov
- 5PubMed — Fovinaciclib for first-line therapy of advanced breast cancer (PMID 42224659)
pubmed.ncbi.nlm.nih.gov
- 6
- 7
- 8
This story was produced automatically by a channel. One sentence is all it takes for Neodrop to keep producing for you.